I take a clinical problem from the first conversation to a working interface. I bring the questions of a pharmacist, the rigor of an engineer, and the willingness to build.
Selected work / 2025-2026 Clinical tools, product thinking & implementation
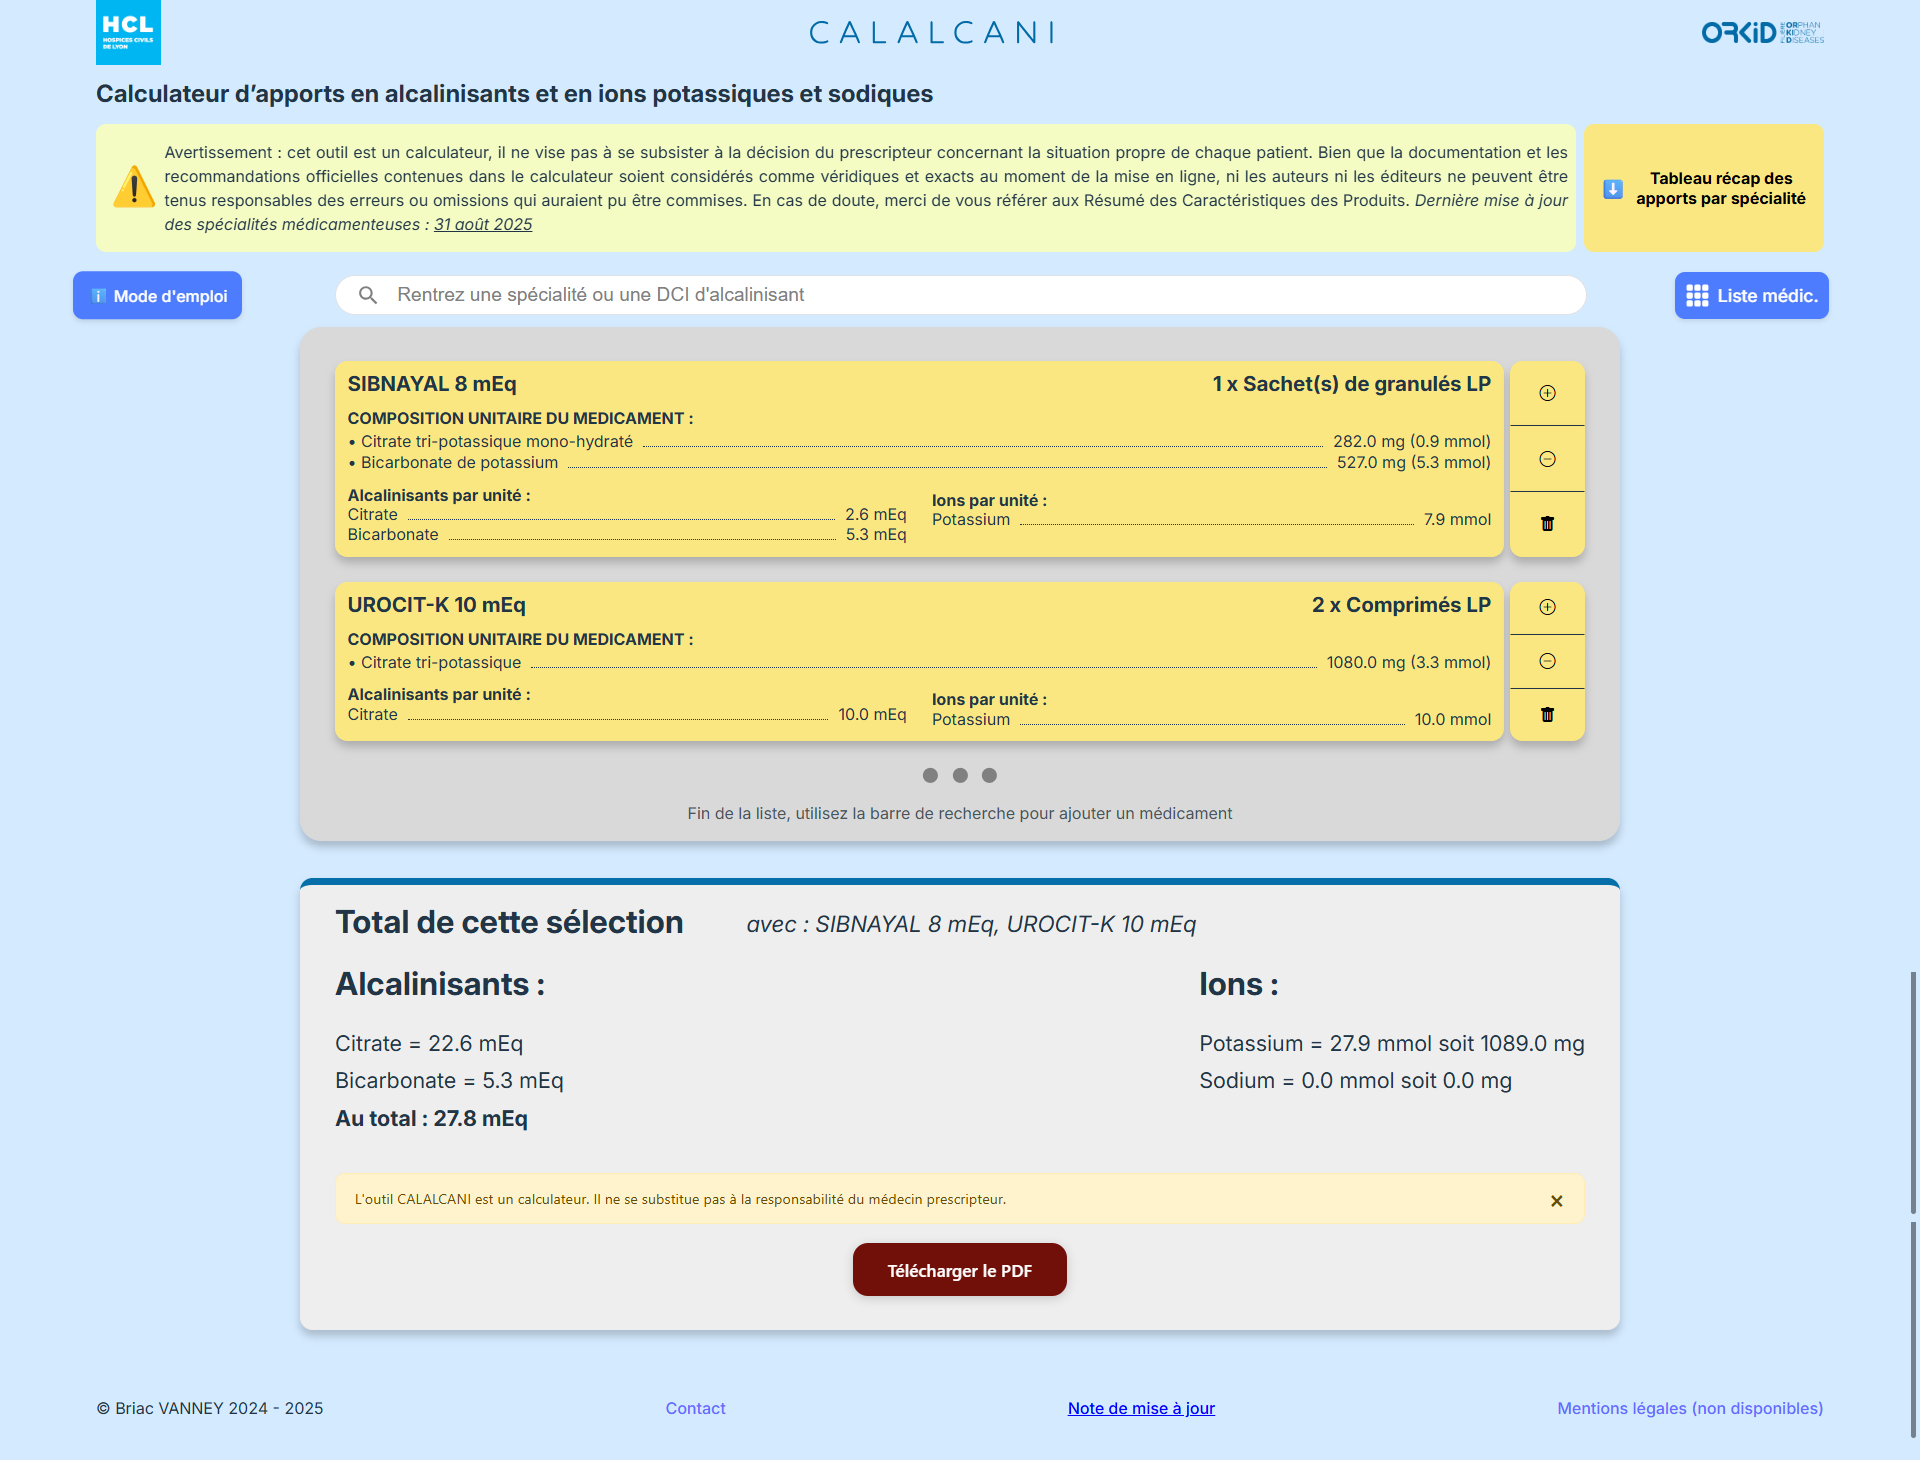
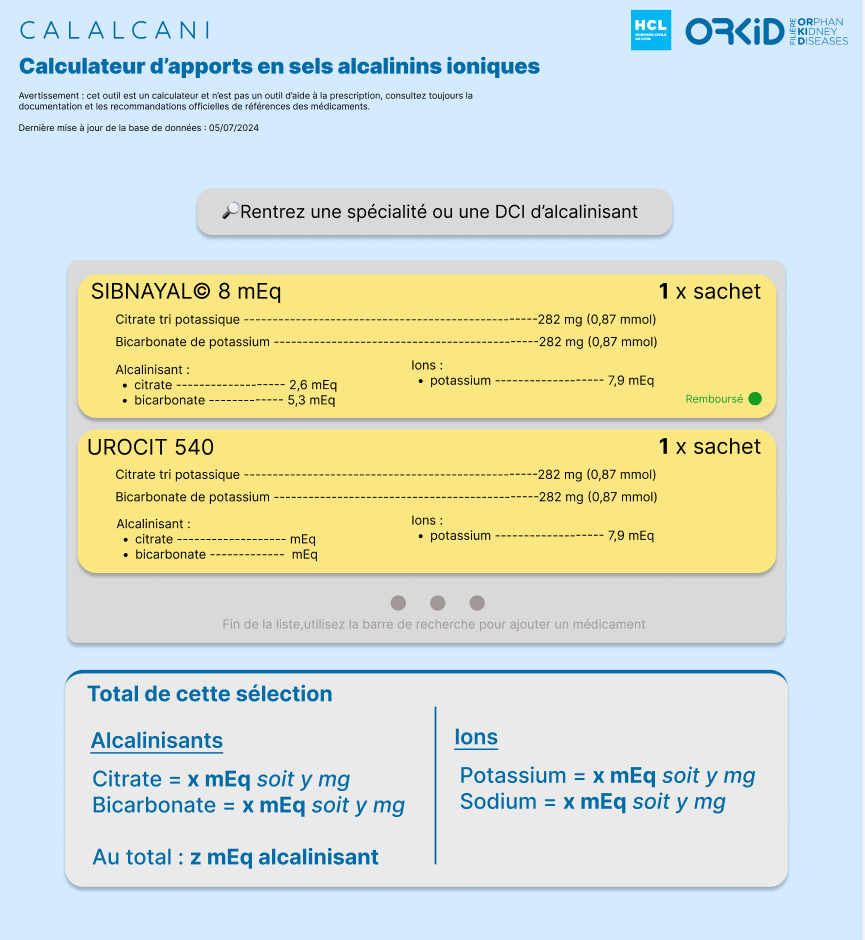
Alkalinizing medications come in different formulations and units. Clinicians need to compare their alkalinizing, sodium, and potassium contributions without losing track of what each medication adds.
The interface needed to make those relationships readable while leaving the clinical decision with the physician.
My contribution
I proposed it, then built it.
I proposed the roadmap and Figma mockup for physician review, structured the medication information and calculation logic, and built the React/JavaScript interface.
I worked with a nephrologist and a pharmacist, incorporated feedback from roughly ten nephrologists, and added guidance and downloadable summaries. I stayed involved through testing and documentation.
01Understand
Discuss the clinical problem and establish the calculation approach in a spreadsheet.
02Make it tangible
Propose a roadmap and a Figma mockup for physician review.
03Build & check
Implement the interface and check data, calculations, and displayed outputs.
04Improve
Use specialist feedback to clarify the interface and guidance.
Original Figma mockup / thesis p.46
Proposed interface before implementation. Original thesis figure 9.
Implemented interface / thesis p.63
Operational v1.0. Original thesis figure 14. Values shown are historic examples, not treatment instructions.
Design decisions
The compromises were human.
01
Start with a name, not a catalog.
Medication search fits the task of selecting a known product. It reduces the need to scan a long list.
Tradeoff: a clear selection flow still needs readable formulation and unit information. Finding the name is not enough to prevent choosing the wrong variant.
02
Show the parts and the total.
Individual medication cards stay distinct from aggregate contributions, so a clinician can inspect where a total comes from.
Tradeoff: more visible information can add clutter. Grouping and hierarchy matter more than removing useful context.
03
Keep help close to the task.
An integrated guide and downloadable summary support understanding and discussion beyond the calculation itself.
Tradeoff: an export is a snapshot. It should not imply that information is still current or replace the clinician’s review.
What I would improve next
Make ambiguity harder to miss.
I would investigate clearer formulation labels, a final review step, and explicit data-version information. I would observe clinicians completing the same tasks before choosing what to change. These are proposed next steps, not features or outcomes already delivered.
Source: my PharmD thesis, pp.33-34 (project), 45-47 (prototype), 63 (implementation), 64-68 (testing), 69-73 (feedback and improvements). Screens reproduced from the thesis.
02 / Independent concept / October 2026
Evidence, in context.
A source should add clarity without stealing the reader’s place.
Interaction design exploration Working browser prototype Not a Vera product or commission
The design question
How might a clinician inspect the support behind an answer, compare its scope, and return to the same passage without rebuilding their mental context?
The boundary
This independent concept was developed for this application with AI assistance. Its clinical framing draws on my pharmacy training and CALALCANI experience. The scenario is illustrative; clinician testing is a proposed next step.
Read a statement›Open its source›Inspect scope & limitations›Return to the same passage
Try the interactionIllustrative content. No clinical recommendations or real patient data.
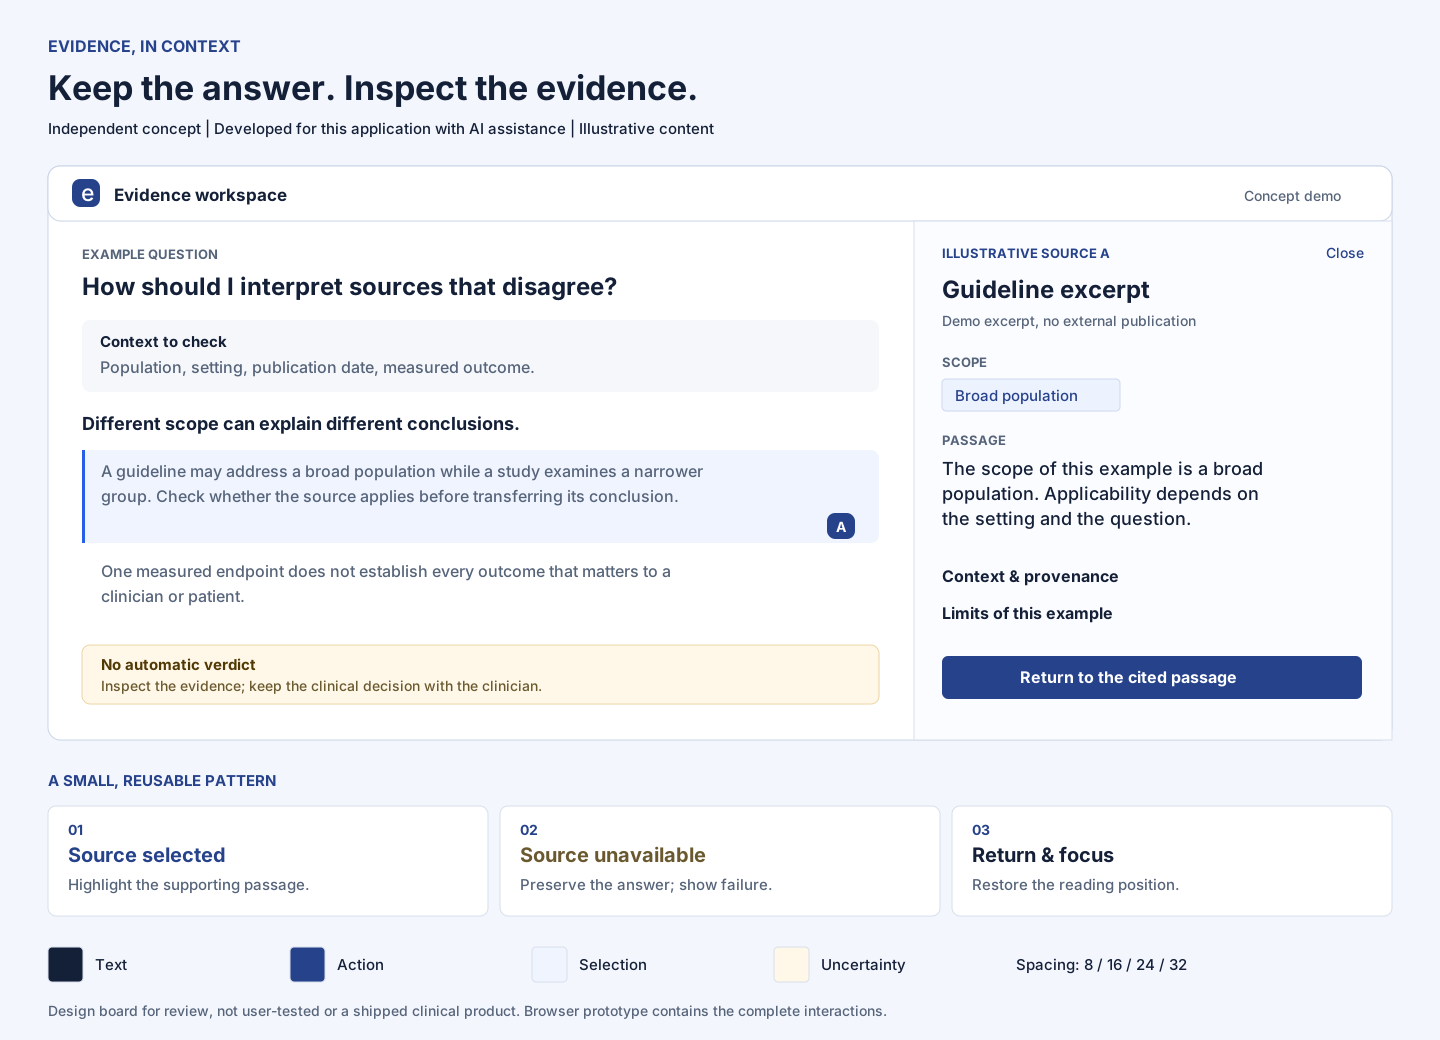
eEvidence workspace
Concept demo
Example question
How should I interpret sources that appear to disagree?
Context to check
Population, setting, publication date, and what the source actually measured.
Different scope can explain different conclusions.
A guideline may address a broad population while a study examines a narrower group. Check whether the source applies to the question before treating its conclusion as transferable.
A finding about one endpoint does not establish every outcome that matters to a clinician or patient. Keep the measured outcome visible when comparing sources.
!
No automatic verdict
This demo helps inspect evidence. It does not resolve a clinical disagreement or recommend treatment.
Select A or B to inspect a source.
What the prototype demonstrates
Speed without hiding the uncertainty.
01
Keep the answer in view.
On desktop, sources open beside the answer. The cited passage stays highlighted. On mobile, the source becomes a focused dialog with a clear return action.
Tradeoff: a split view reduces answer width. The layout changes when it can no longer keep both columns readable.
02
Surface scope before confidence.
The source panel separates excerpt, population, and limitations. It avoids an unsupported confidence percentage or a badge that implies verification.
Tradeoff: this adds reading. Progressive disclosure keeps the essential context visible and lets readers expand the rest.
03
Fail honestly, preserve context.
A missing source stays visibly unavailable. The answer remains accessible, and the reader can retry or return without silently substituting another source.
Tradeoff: the failed path feels less seamless. That friction is preferable to suggesting evidence was checked when it was not.
Proposed evaluation / not conducted
Test the task, not whether people like the screen.
I would begin with six clinicians as an exploratory sample, alternating task order between a separate-source view and this contextual view.
Find which passage a source supports.
Identify a population mismatch.
Return to the original passage after reading a source.
Explain what remains uncertain when a source is unavailable.
Measure task completion, lost-context events, misunderstandings, and time to return. Six participants would reveal usability issues, not establish clinical safety or generalizable outcomes.
Implementation decisions
Details are part of the design.
Source selection and the cited passage share the same state.
Closing restores keyboard focus to the originating control.
Escape closes the panel; mobile focus stays inside the source dialog.
Source content has its own reading hierarchy and expandable limits.
An unavailable state is distinct from a source with evidence limitations.
The working prototype uses HTML, CSS, and JavaScript. The design specifies source states, reading hierarchy, responsive behavior, and keyboard interaction.
I ask the clinical questions. I follow through on the build.
I'm a doctor of pharmacy and biomedical engineer based in Lyon. At Onicor, I analyzed usability data in Python, examined methodological limitations, interviewed two podiatrists about adoption barriers, and created scientific communication materials.
My pharmacy training included laboratory practicals. It taught me to question the measurement, the method, and the conclusion. I bring that habit to product work: check what was measured before deciding what the result means.
I work in French and English. I'm looking for a demanding team where I can learn quickly, get direct feedback, and take responsibility for a useful product.